 Simulated
Loading the scans…
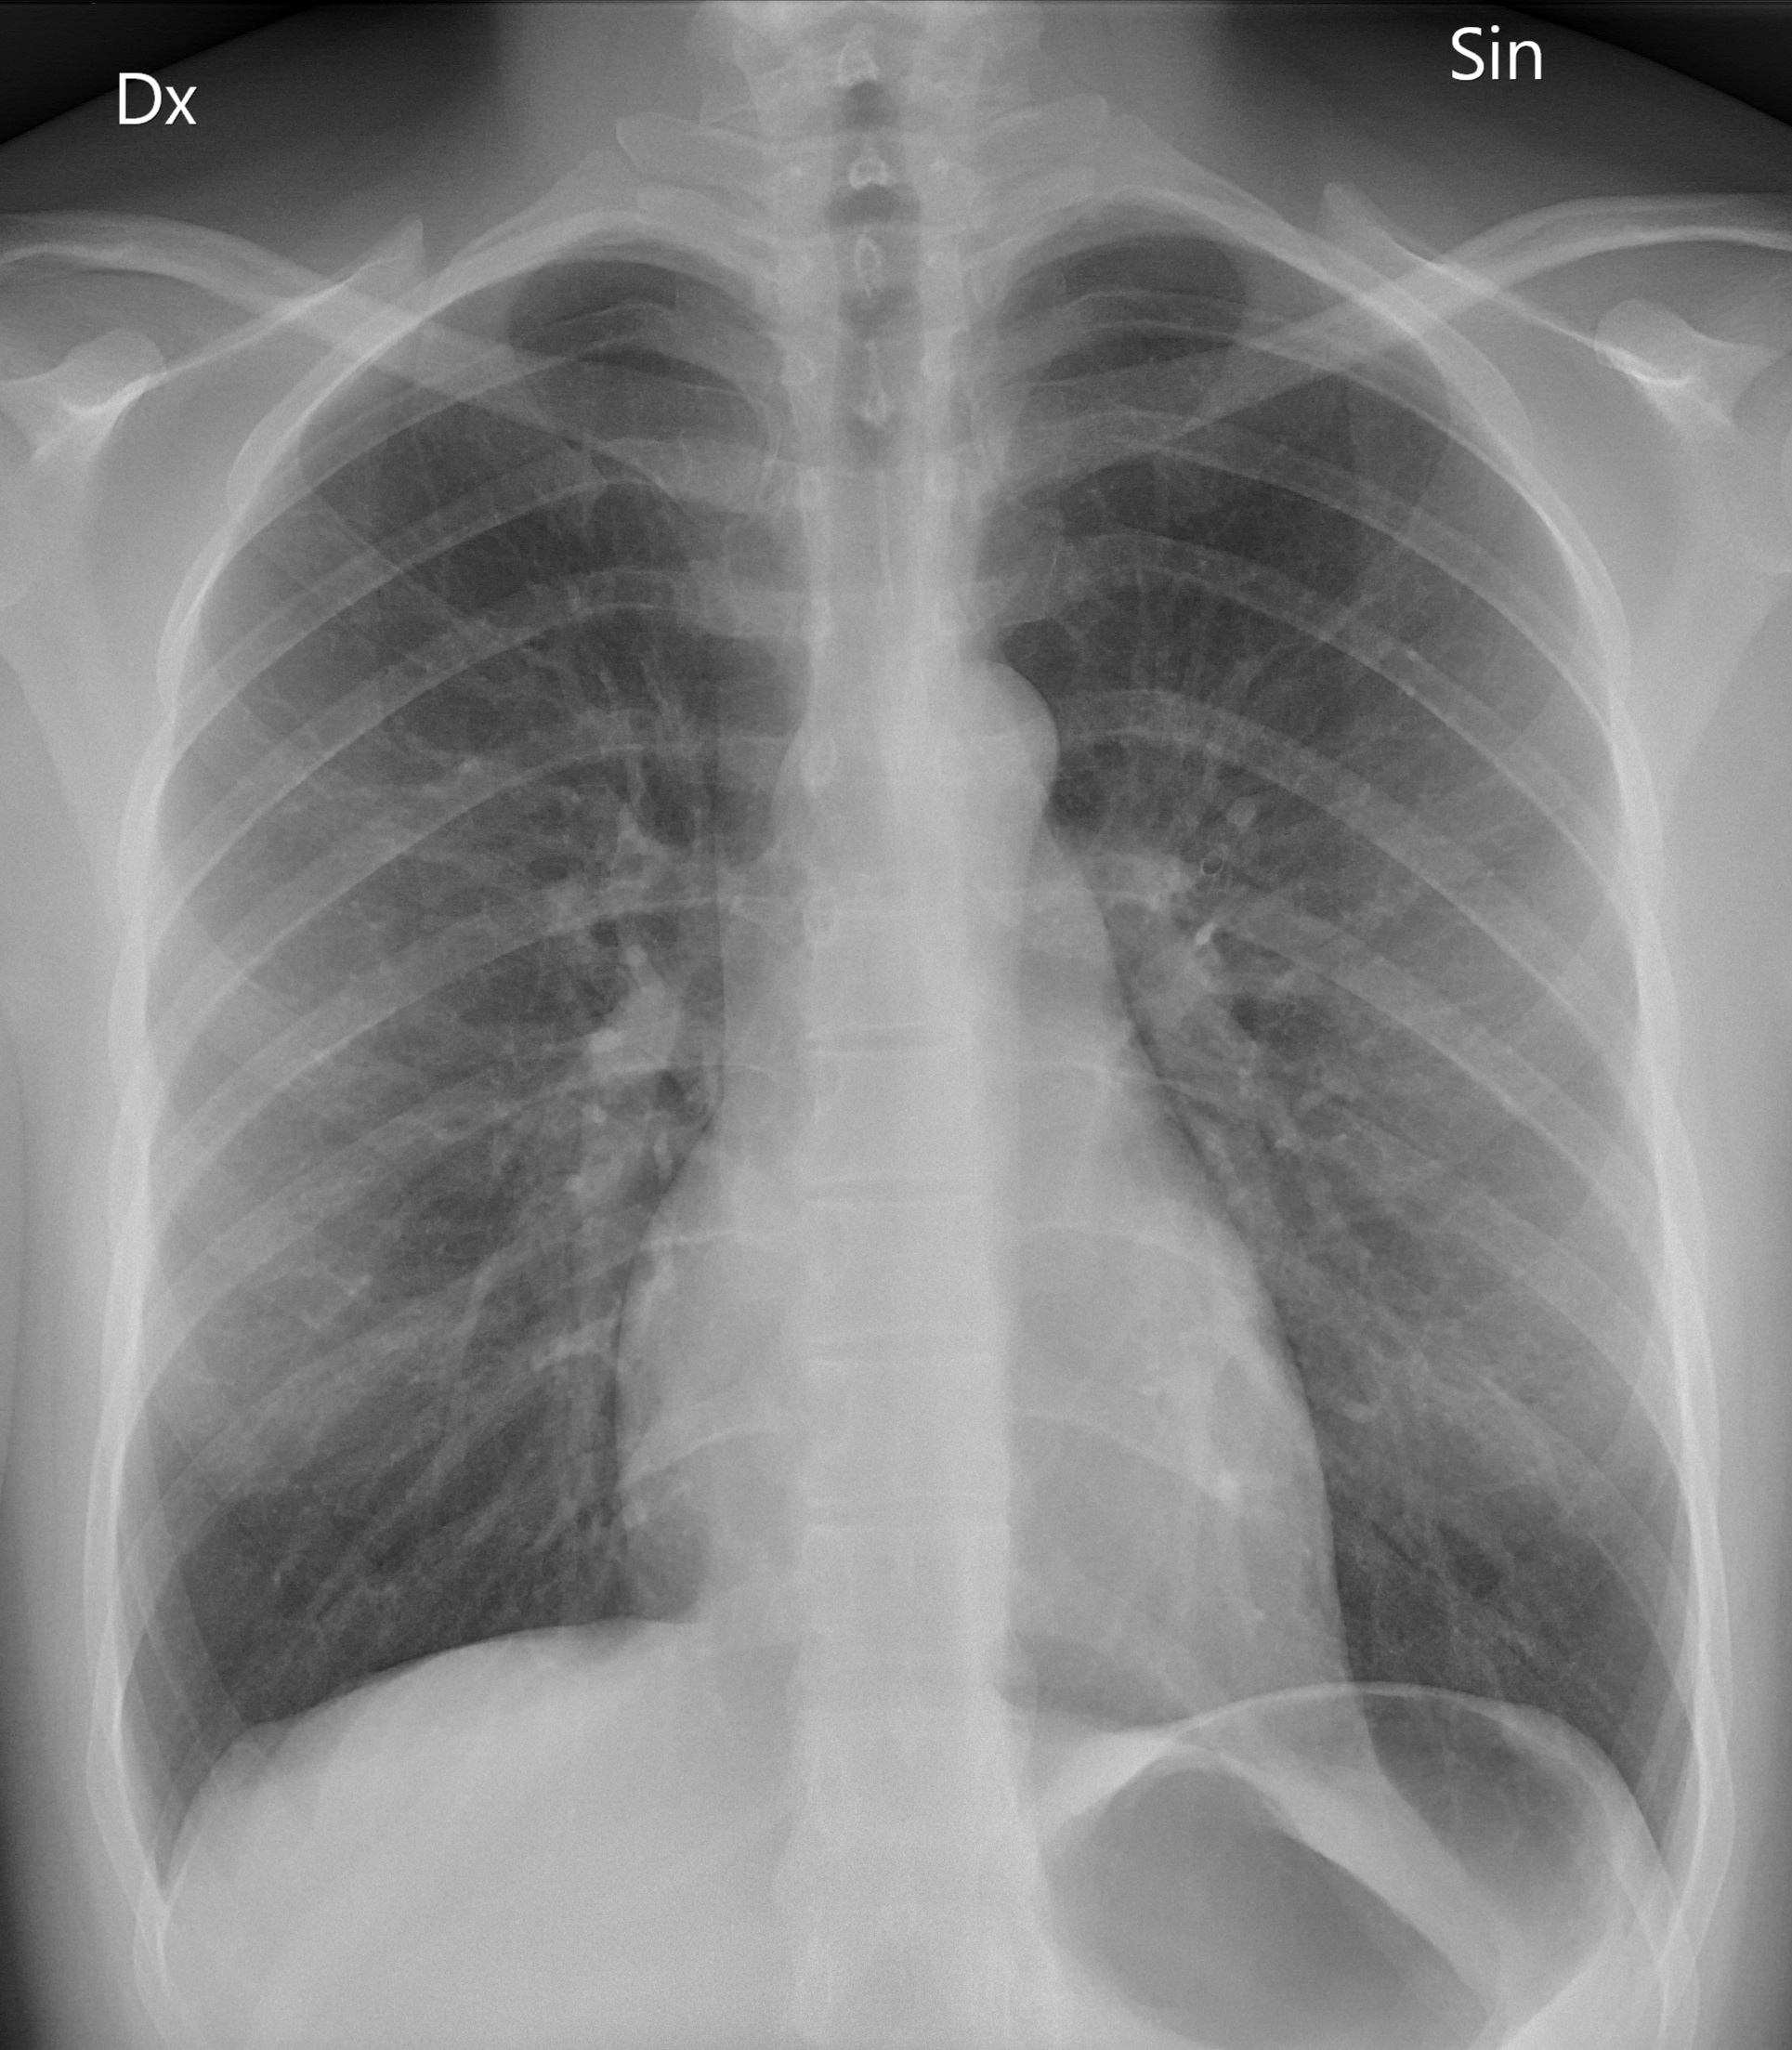
Real PA chest radiograph of another person (Mikael Häggström, CC0), shown unaltered; its technique is not known. Its markers Dx and Sin mean right and left (Latin dexter, sinister).
These numbers are for the simulated image; the real radiograph's technique is not known.
| Quantity | Reference | Now | Change |
|---|
Last change: change a setting to see what it does to each row.
Incident air kerma (at the skin) is the air kerma at the skin, free in air, so it excludes backscatter: tube output × mAs × the inverse square of the distance to the skin (IAEA handbook eq. 22.16; Junda 2021, eq. 2). EI is 100 × the air kerma at the detector in µGy (IEC definition). Both come from the model, calibrated to 52.4 µGy per mAs at 80 kVp and 1 m; real units differ. Changing the examination resets the reference: a comparison across patients means nothing.
Try this
- Exposure creep. Double the mAs twice. The processed image barely changes, except that it looks less noisy, while the deviation index climbs and the incident air kerma quadruples. Switch to Unprocessed to see it with fixed, film-like grey levels.
- Too little. Halve the mAs three times. Brightness stays the same on the processed image; noise and a negative deviation index give it away.
- kVp and contrast. On the chest, compare 70 kVp with 120 kVp, adjusting mAs to keep the deviation index near 0. Bone contrast falls at the higher kVp, and the beam gets through the mediastinum more easily.
- Grid. On the abdomen, remove the grid: scatter adds a haze and contrast drops, and the exposure index rises because the grid no longer absorbs any of the beam.
- Distance. Move from 100 cm to 180 cm and watch the deviation index fall: the mAs needs to rise by (180/100)², about 3.2 times, to match.
- Air gap. Add a 20 cm air gap and watch the magnification and focal-spot blur readouts grow; the blur is too small to see here, and the scatter reduction from an air gap is not modelled.
How the image is made
Each radiograph is computed through a real CT scan. Every voxel of the patient is split into water-like tissue, fat and bone from its CT number, read at an assumed effective energy of 60 keV; the split rule is a modelling choice, not a published conversion. For each point of the detector, the simulator follows the X-ray beam front to back through those tissues at every photon energy. It uses an idealised Kramers-type spectrum for a tungsten target (no characteristic lines) for the chosen kVp and filtration, and attenuation coefficients computed from the EPICS2025 photon data of Lawrence Livermore National Laboratory. Tube output is calibrated to 52.4 µGy per mAs at 80 kVp and 1 m. The starting mAs comes from a simplified automatic exposure control: it brings the mean air kerma over the central third of the detector to 2.5 µGy, to the nearest step of the mAs slider, whereas a real system measures with chambers. Scatter is added as a smooth haze: its amount matches phantom measurements with and without a grid (IAEA Table 6.3), and its spread, a 30 mm blur, is a display choice. The deviation index compares the air kerma reaching the detector with the target exposure.
What the simulator leaves out
- The CT voxels are 1.5 mm, so the image is softer than a real radiograph and focal-spot blur, which is smaller than that, cannot be seen; the readout gives its size instead.
- The patient lies supine as on the CT table, and arms are removed where they are separate from the trunk. Beams are parallel, so enlargement is uniform (real beams diverge) and the heart's extra magnification on an AP film is not modelled.
- The chest CT was taken supine at the CT breath-hold, so lung volume and diaphragm position differ from an erect radiograph at full inspiration.
- CT numbers are read at an assumed effective energy of 60 keV (an assumption, not a sourced value). The abdomen CT was scanned at 80 kVp, where the effective energy is lower, so bone may be overstated on the abdomen.
- The Kramers spectrum has no characteristic lines, and it is softer than a real tube's, so the simulator uses 4.5 mm aluminium-equivalent filtration, the least that meets the FDA minimum half-value layers to the nearest 0.5 mm.
- The FDA table (21 CFR 1020.30, Table 1) groups its minimum half-value layers by the system's designed operating range. This page picks the group from the set kVp, which is its own reading of the table.
- An ideal detector that absorbs every photon; no heel effect; the scatter-reducing effect of an air gap and the effect of field size on scatter.
- The exposure index uses the IEC definition (100 × air kerma at the detector in µGy), which assumes the RQA5 test beam; real systems read differently for other beams and vendors. The noise level at the starting technique is a display choice.